

Key takeaways
- HCA Florida JFK Hospital added two Relay delivery robots in September 2026 for routine internal transport.
- Hospital robots must integrate with elevators, secure doors, fire systems, and IT, not just hallways.
- Relay cites 8 to 12 week typical deployments with 1 to 2 weeks onsite installation.
- Florida systems can pilot one corridor or department before scaling fleet-wide transport.
- Service Robot Co. can finance, integrate, train, and service delivery robots as one vendor.
Why are Florida hospitals adding corridor delivery robots now?
On September 30, 2026 Relay Robotics announced that HCA Florida JFK Hospital in Atlantis deployed two autonomous delivery units named Dash and Daisy. The goal is familiar across acute care: keep medications, lab specimens, telemetry gear, and pharmacy orders moving without pulling nurses and techs off the unit for every short trip.
Florida hospitals face the same staffing pressure as the rest of the country, plus hurricane-season logistics that can disrupt supply runs and vendor access. A mapped delivery robot does not replace clinical judgment, but it can cover repeatable point-to-point routes while humans stay with patients.
For operators watching this rollout, the lesson is less about the brand on the robot and more about whether your building systems will let a machine cross floors and secure zones safely.
Atlantis sits in Palm Beach County between major tourist corridors and retirement communities, so JFK serves a mix of emergency, surgical, and medical-surgical volume. That profile creates steady internal traffic even when census is flat, which is why small delivery trips add up.
What trips are Dash and Daisy built to handle?
Relay describes the JFK deployment as support for lab specimen runs, pharmacy orders, telemetry and monitoring equipment, and medication or lab material moves where pneumatic tubes do not reach. Those are high-frequency, time-sensitive tasks that still feel low value when a licensed clinician makes the walk.
Authorized staff load a secured compartment, pick a destination, and the robot navigates with LiDAR, sensors, and computer vision. At the receiving unit, authorized staff retrieve the item. That workflow keeps chain-of-custody visible compared with leaving a cart in a hallway.
If your hospital still moves coolers, blood tubes, or IV bags by hand several times per shift, list those routes before you talk hardware. The best pilot lane is the one nurses already resent.
Relay also notes emergency departments depend on timely specimen and medication movement. Even if JFK starts elsewhere, ED leaders will ask whether a robot can survive peak noise, gurney traffic, and frequent door cycles without blocking egress.

Why do elevators and secure doors matter more than speed?

Relay notes that this deployment required coordination across elevators, secure doorways, fire and life-safety systems, and hospital IT. That is the difference between a demo in a conference room and a live patient tower.
A robot that cannot call an elevator or trigger an approved door will fail on paper at a two-campus Florida medical center. Mapping must include badge-controlled entries, restricted pharmacy corridors, and after-hours lock schedules.
CEO Sultan Mehrabi framed the JFK project as proof that large health systems can integrate all of those layers at once. Your team should ask every vendor for a written integration scope, not a hallway video.
Plan tabletop exercises with facilities, biomedical engineering, and cybersecurity before hardware arrives. Elevator vendors, door controllers, and nurse call systems each have change-control rules that can delay a go-live if you discover them during installation week.
How long should Florida hospitals budget for go-live?
Relay publishes a typical hospital timeline of about eight to twelve weeks including integration hardware, floor mapping, and staff training, with onsite installation often taking one to two weeks. Florida facilities with older elevator controllers or mixed vendor doors should plan reviews early.
Phase the work: document routes, validate infection-control wipe-down steps, run shadow mode with a facilities escort, then open one department at a time. Emergency departments and perioperative areas are tempting, but they are also the noisiest environments for a first map.
Service Robot Co. stays OEM-neutral, so the schedule should follow your infrastructure reality rather than a single robot datasheet.
Build a steering committee that meets weekly during integration. Include pharmacy, lab, nursing leadership, EVS, and IT security so decisions do not bottleneck in facilities alone.
What changes for infection control and cleaning?
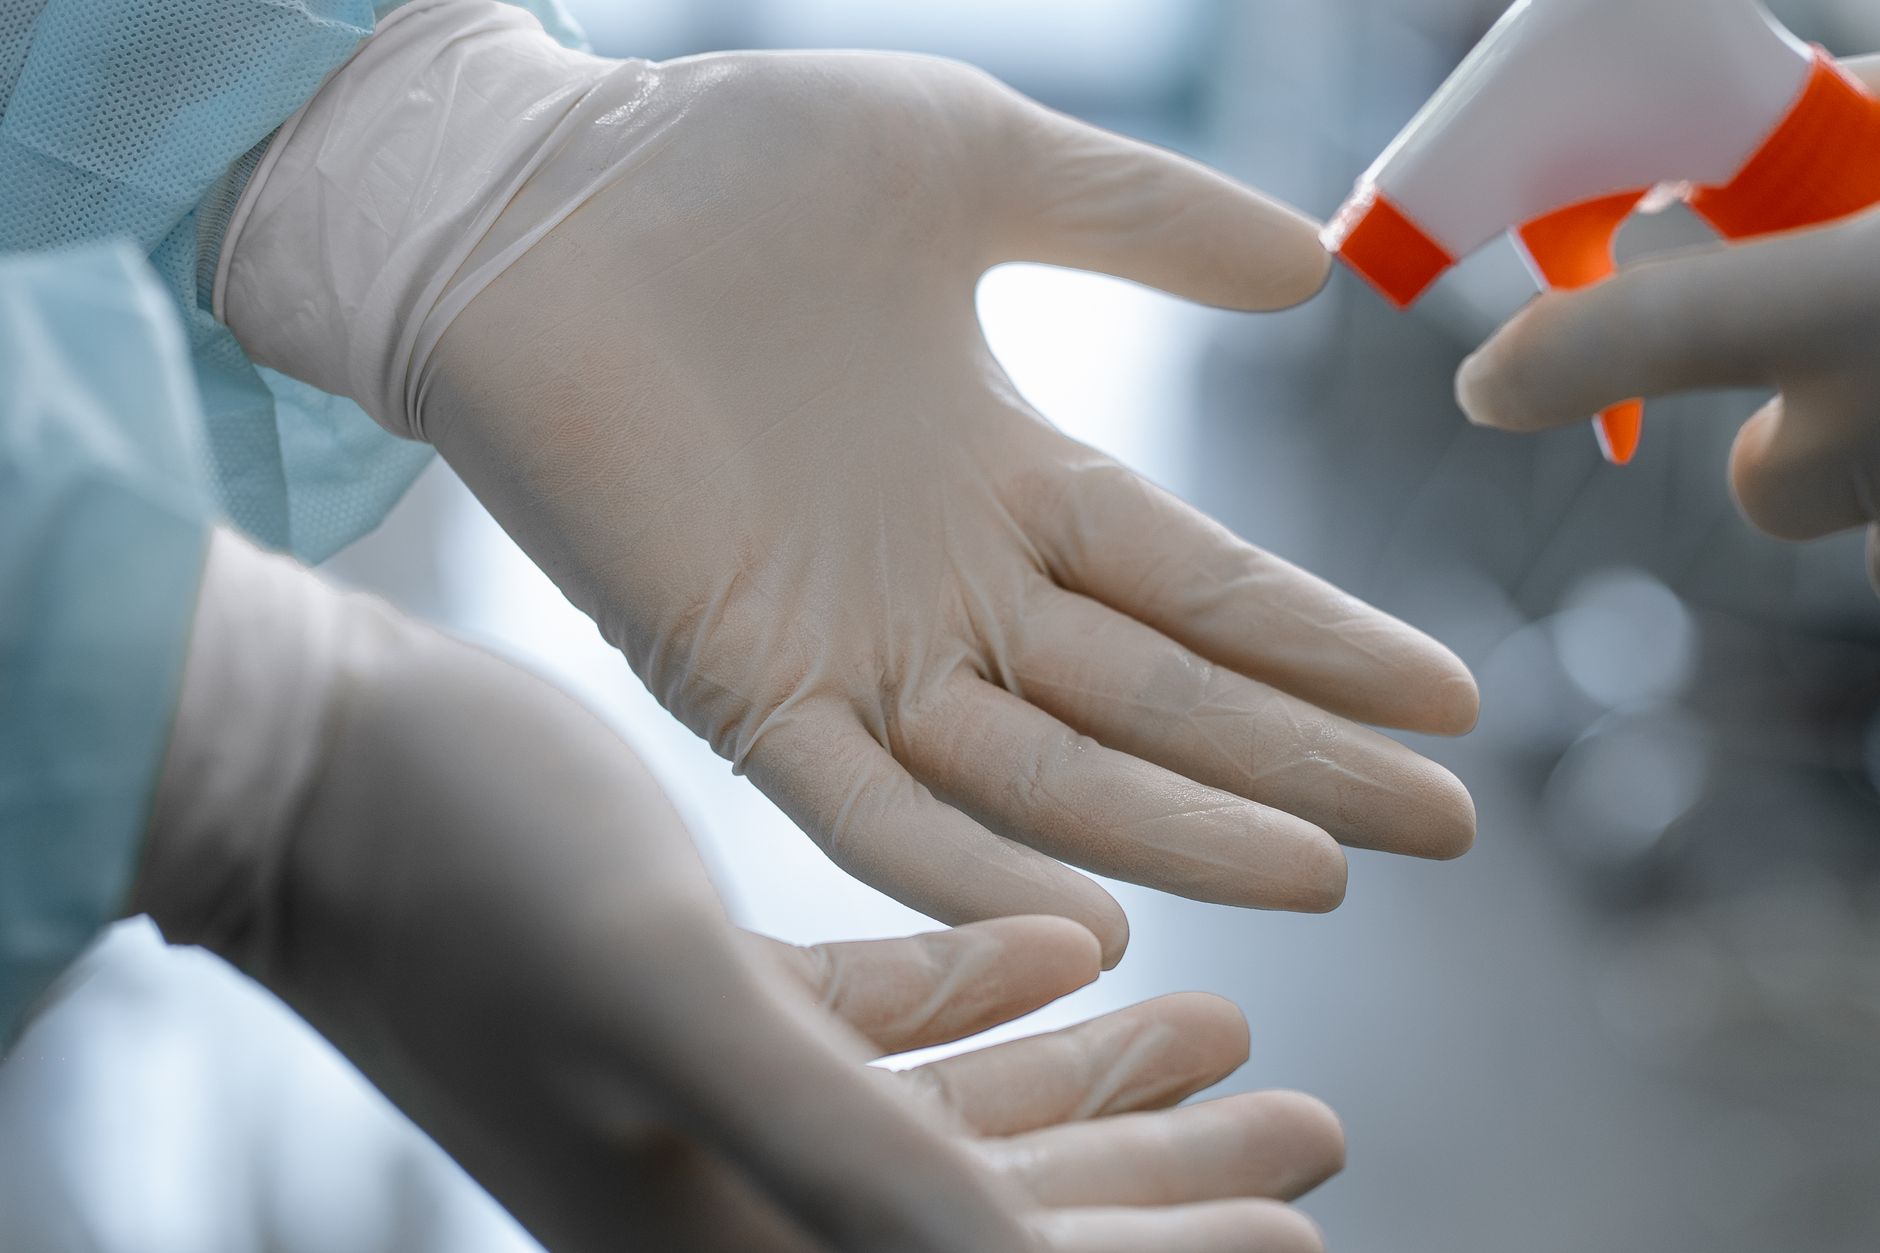
Relay highlights contact-free handoffs and surfaces that support hospital wipe-down protocols. Your environmental services team should sign off on cleaners and dwell times before units enter isolation-adjacent corridors.
Treat robots like mobile carts: define who wipes them between trips, when a unit pauses for a spill, and how you log that in your existing quality checklist. Robotics does not remove documentation, it adds a moving asset to the list.
If you run a Florida system with strict Joint Commission survey prep, bake the robot into your tracer stories now, not the week before auditors arrive.
Train staff on when to refuse a robot trip, such as during active isolation cleaning or when a hallway is wet after floor work. Clear stop rules prevent both infection-control drift and nuisance tickets to the help desk.
Where do robots complement pneumatic tube systems?
Tubes excel at small payloads between fixed stations. They fail when a unit sits off the network, when equipment is bulky, or when a new wing has not been tied into the legacy loop.
Relay explicitly positions robots for tube-free zones. That is common in older Florida hospitals that added patient towers without extending pneumatic infrastructure.
Model cost per trip, not just capital cost. A robot that covers three tube-free routes on night shift may pay back faster than another capital project to extend carriers through concrete decks.
Document which items stay on tubes forever versus which items move to robots. Pharmacy leaders will want guardrails so controlled substances never ride in an unsecured compartment.
What should you measure in the first ninety days?
Track completed trips, failed trips, average turnaround time, and how many clinical hours you reclaim per week. Relay cites more than 99 percent delivery reliability and a 99.8 percent success rate across more than 30 major U.S. hospitals, but your floor will write its own scorecard.
Survey nurses and lab staff separately. Facilities may love the robot while clinical teams ignore it if loading steps feel clumsy.
Log elevator wait times and door denial events. Those two metrics predict whether you can scale beyond the pilot corridor.
Compare robot trips to historical pager logs or manual run sheets if you have them. Hard data beats hallway anecdotes when you ask for funding to add a third unit.
How does a single integrator reduce risk for multi-site rollouts?
Large Florida systems rarely want a different integrator in every county. Service Robot Co. selects delivery hardware across manufacturers, lines up buy or lease financing, maps routes with your IT and facilities teams, trains staff, and supports units through RoboCare with regional service engineers.
Relay's JFK story is a reference for complex integration, not a template you copy without site walks. Your tower may need different door vendors than a Gulf Coast community hospital.
Start with a scoped pilot, document integration lessons, then scale with the same playbooks and service number instead of renegotiating from scratch.
When you expand, reuse elevator and door integration patterns where controllers match, but still remap every floor. Copying a map from Atlantis to a Tampa campus without a fresh walk is how robots end up in a fire stairwell on day one.
Frequently asked questions
Sources
Service Robot Co. is not affiliated with, sponsored by, or endorsed by the companies mentioned in this article.


